Primary Survey
- Call early for a senior doctor to help
- Assess airway patency
- Exclude airway obstruction and asphyxia
- Start monitoring (pulse oximetry, ECG, BP)
- Assess breathing:
- Oxygenation (saturation probe)
- Ventilation (end tidal CO2, chest auscultation)
- Exclude tension pneumothorax and massive haemothorax
- Assess circulation
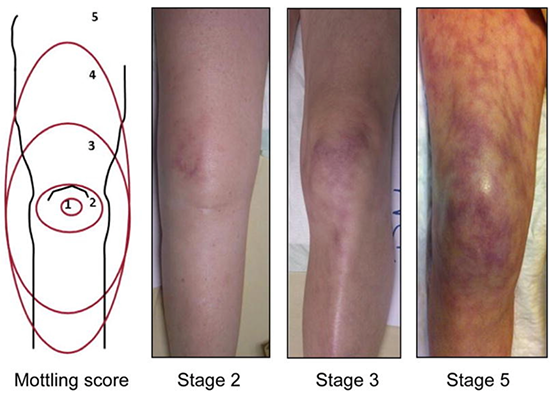
- Peripheral and central temperature/capillary refill
- Vital signs (heart rate, blood pressure)
- Equipment check
- Exclude artifactual shock and equipment failure as the cause of shock, e.g. IABP malfunction, ECMO circuit problems, vasopressor infusion drug error.
- Head-to-toe exposure
- Exclude externally obvious haemorrhage
- Exclude anaphylaxis/angioedema
- 12-lead ECG
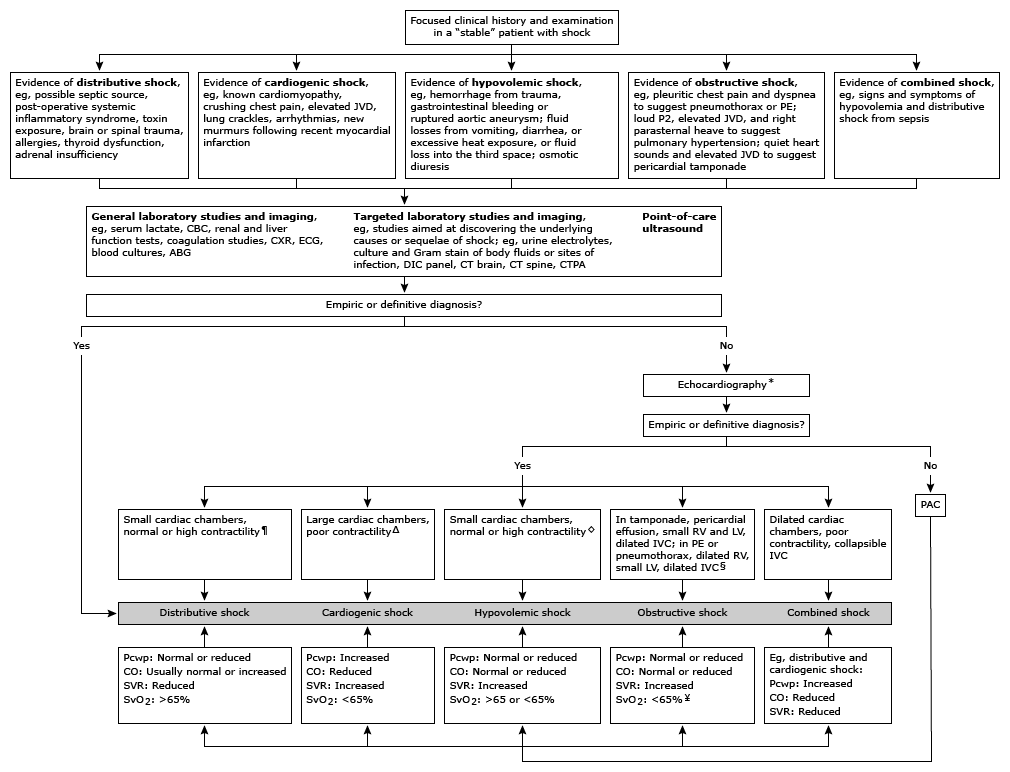
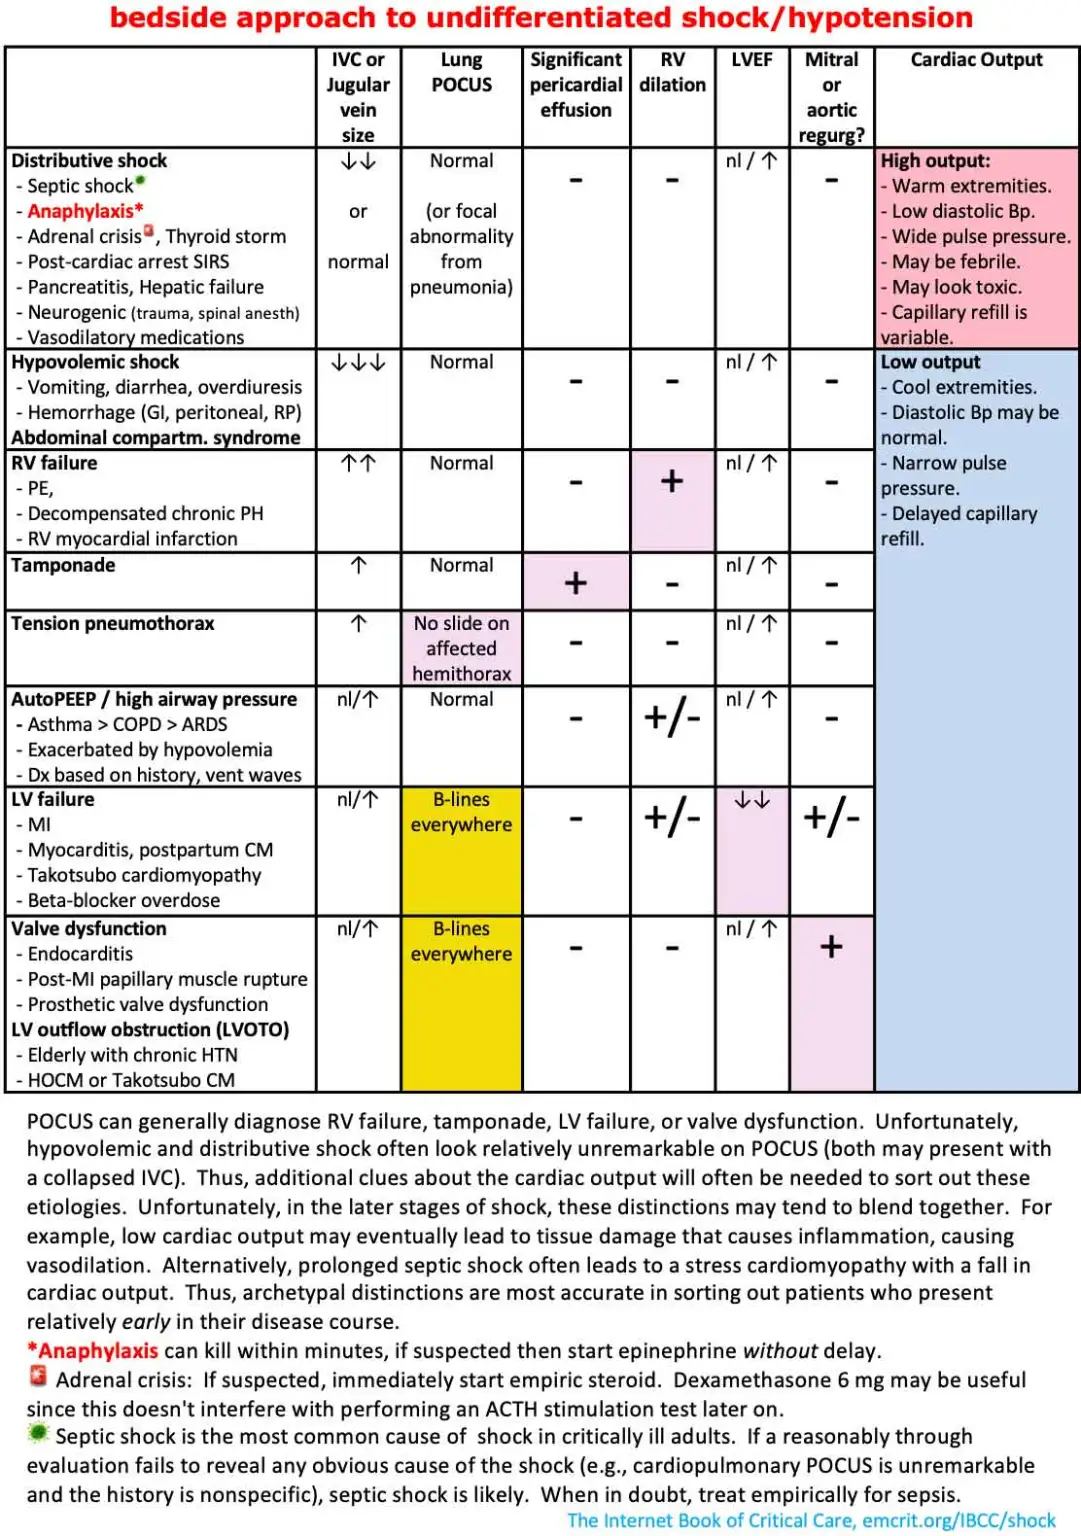
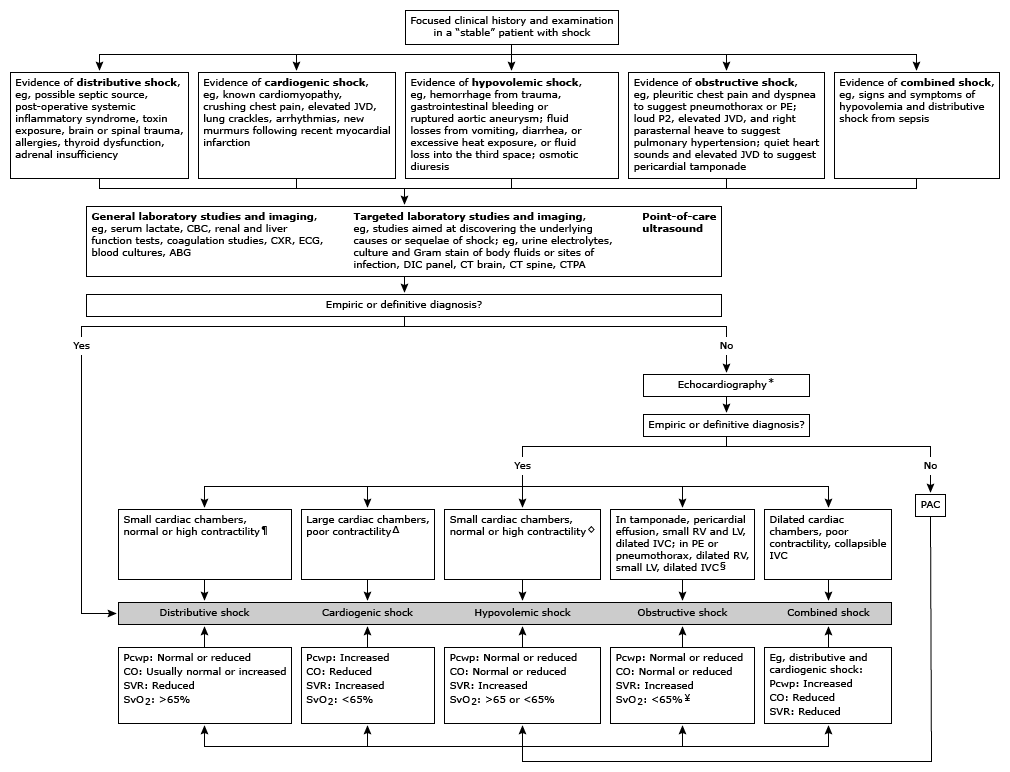
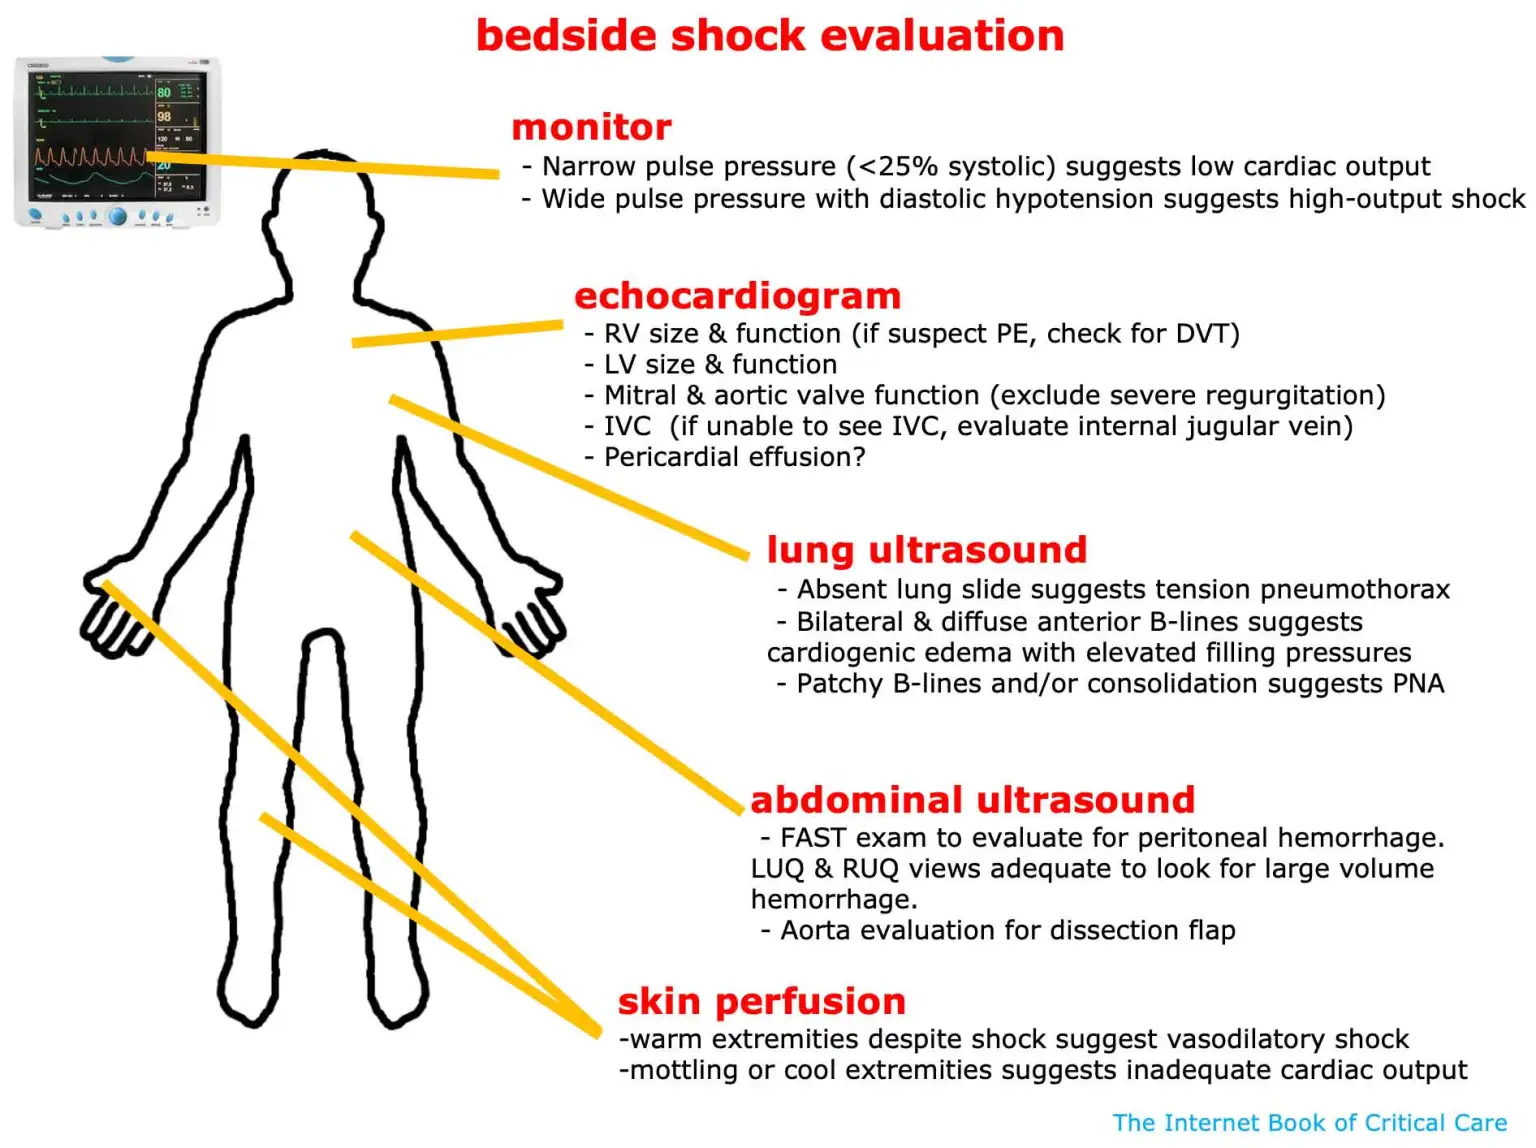
- Point of care TTE: rapid assessment with cardiac echo and RUSH exam
- Exclude cardiac tamponade
- Exclude massive PE
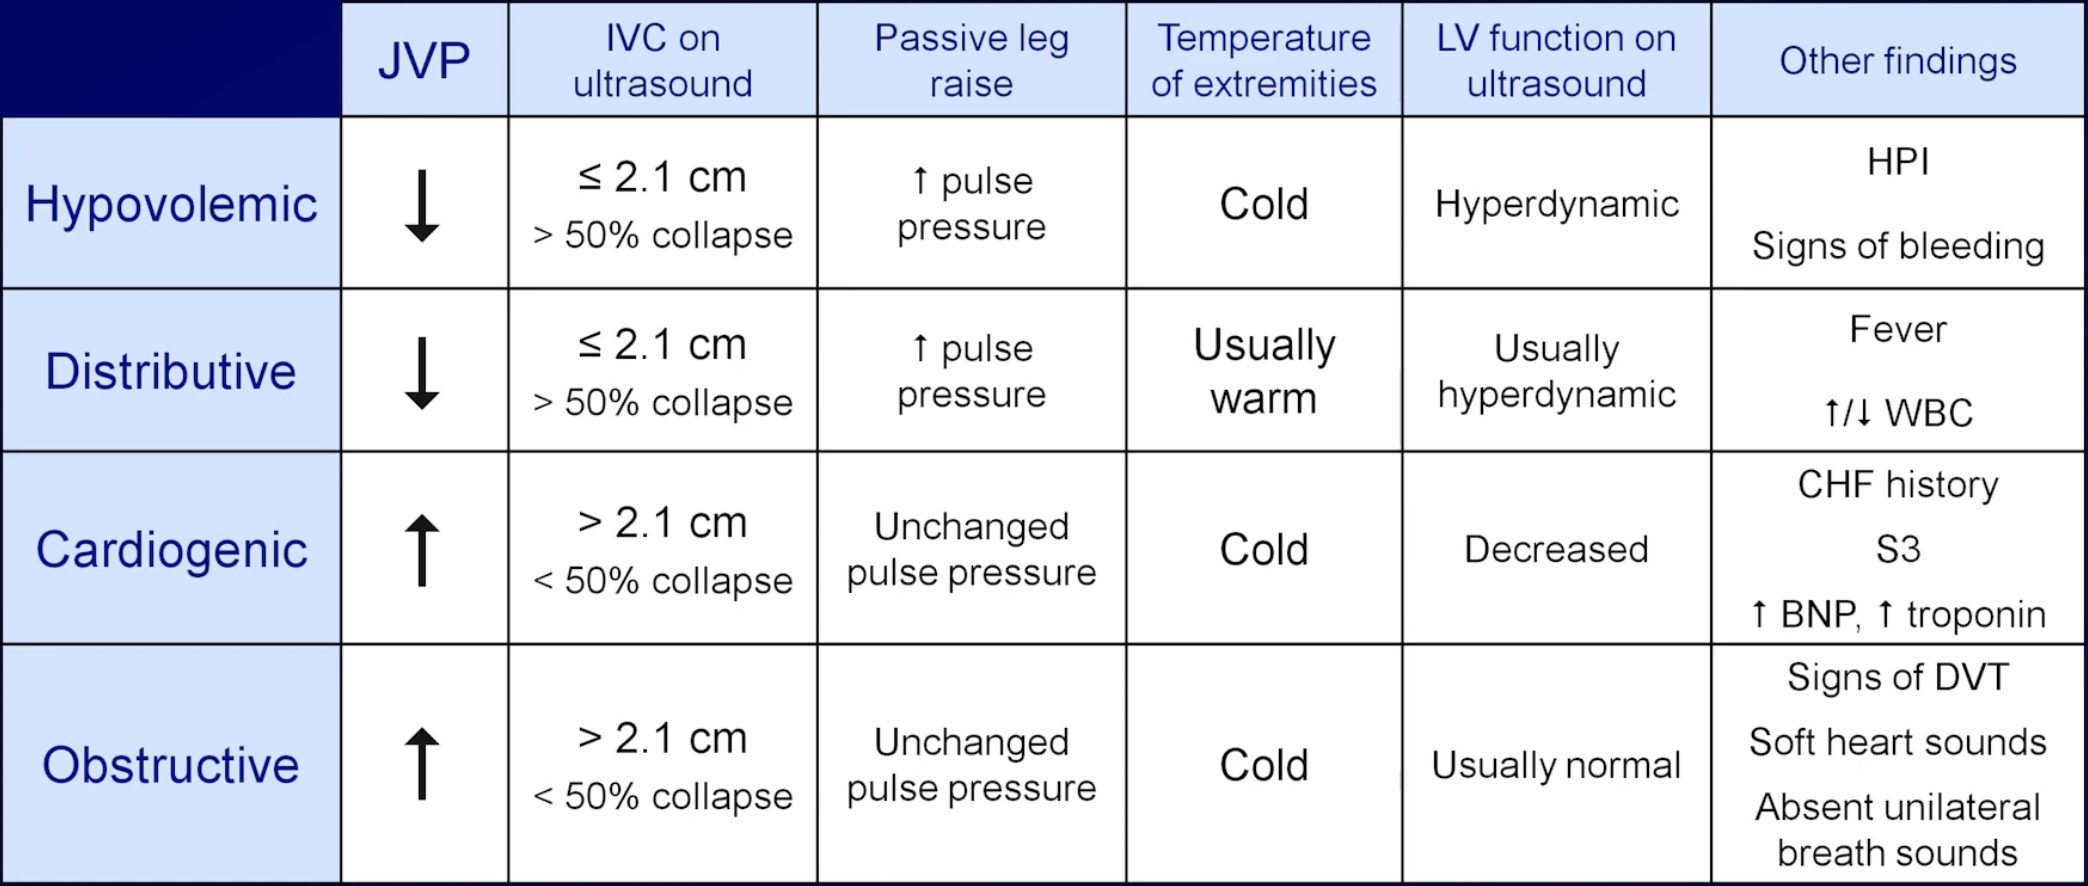
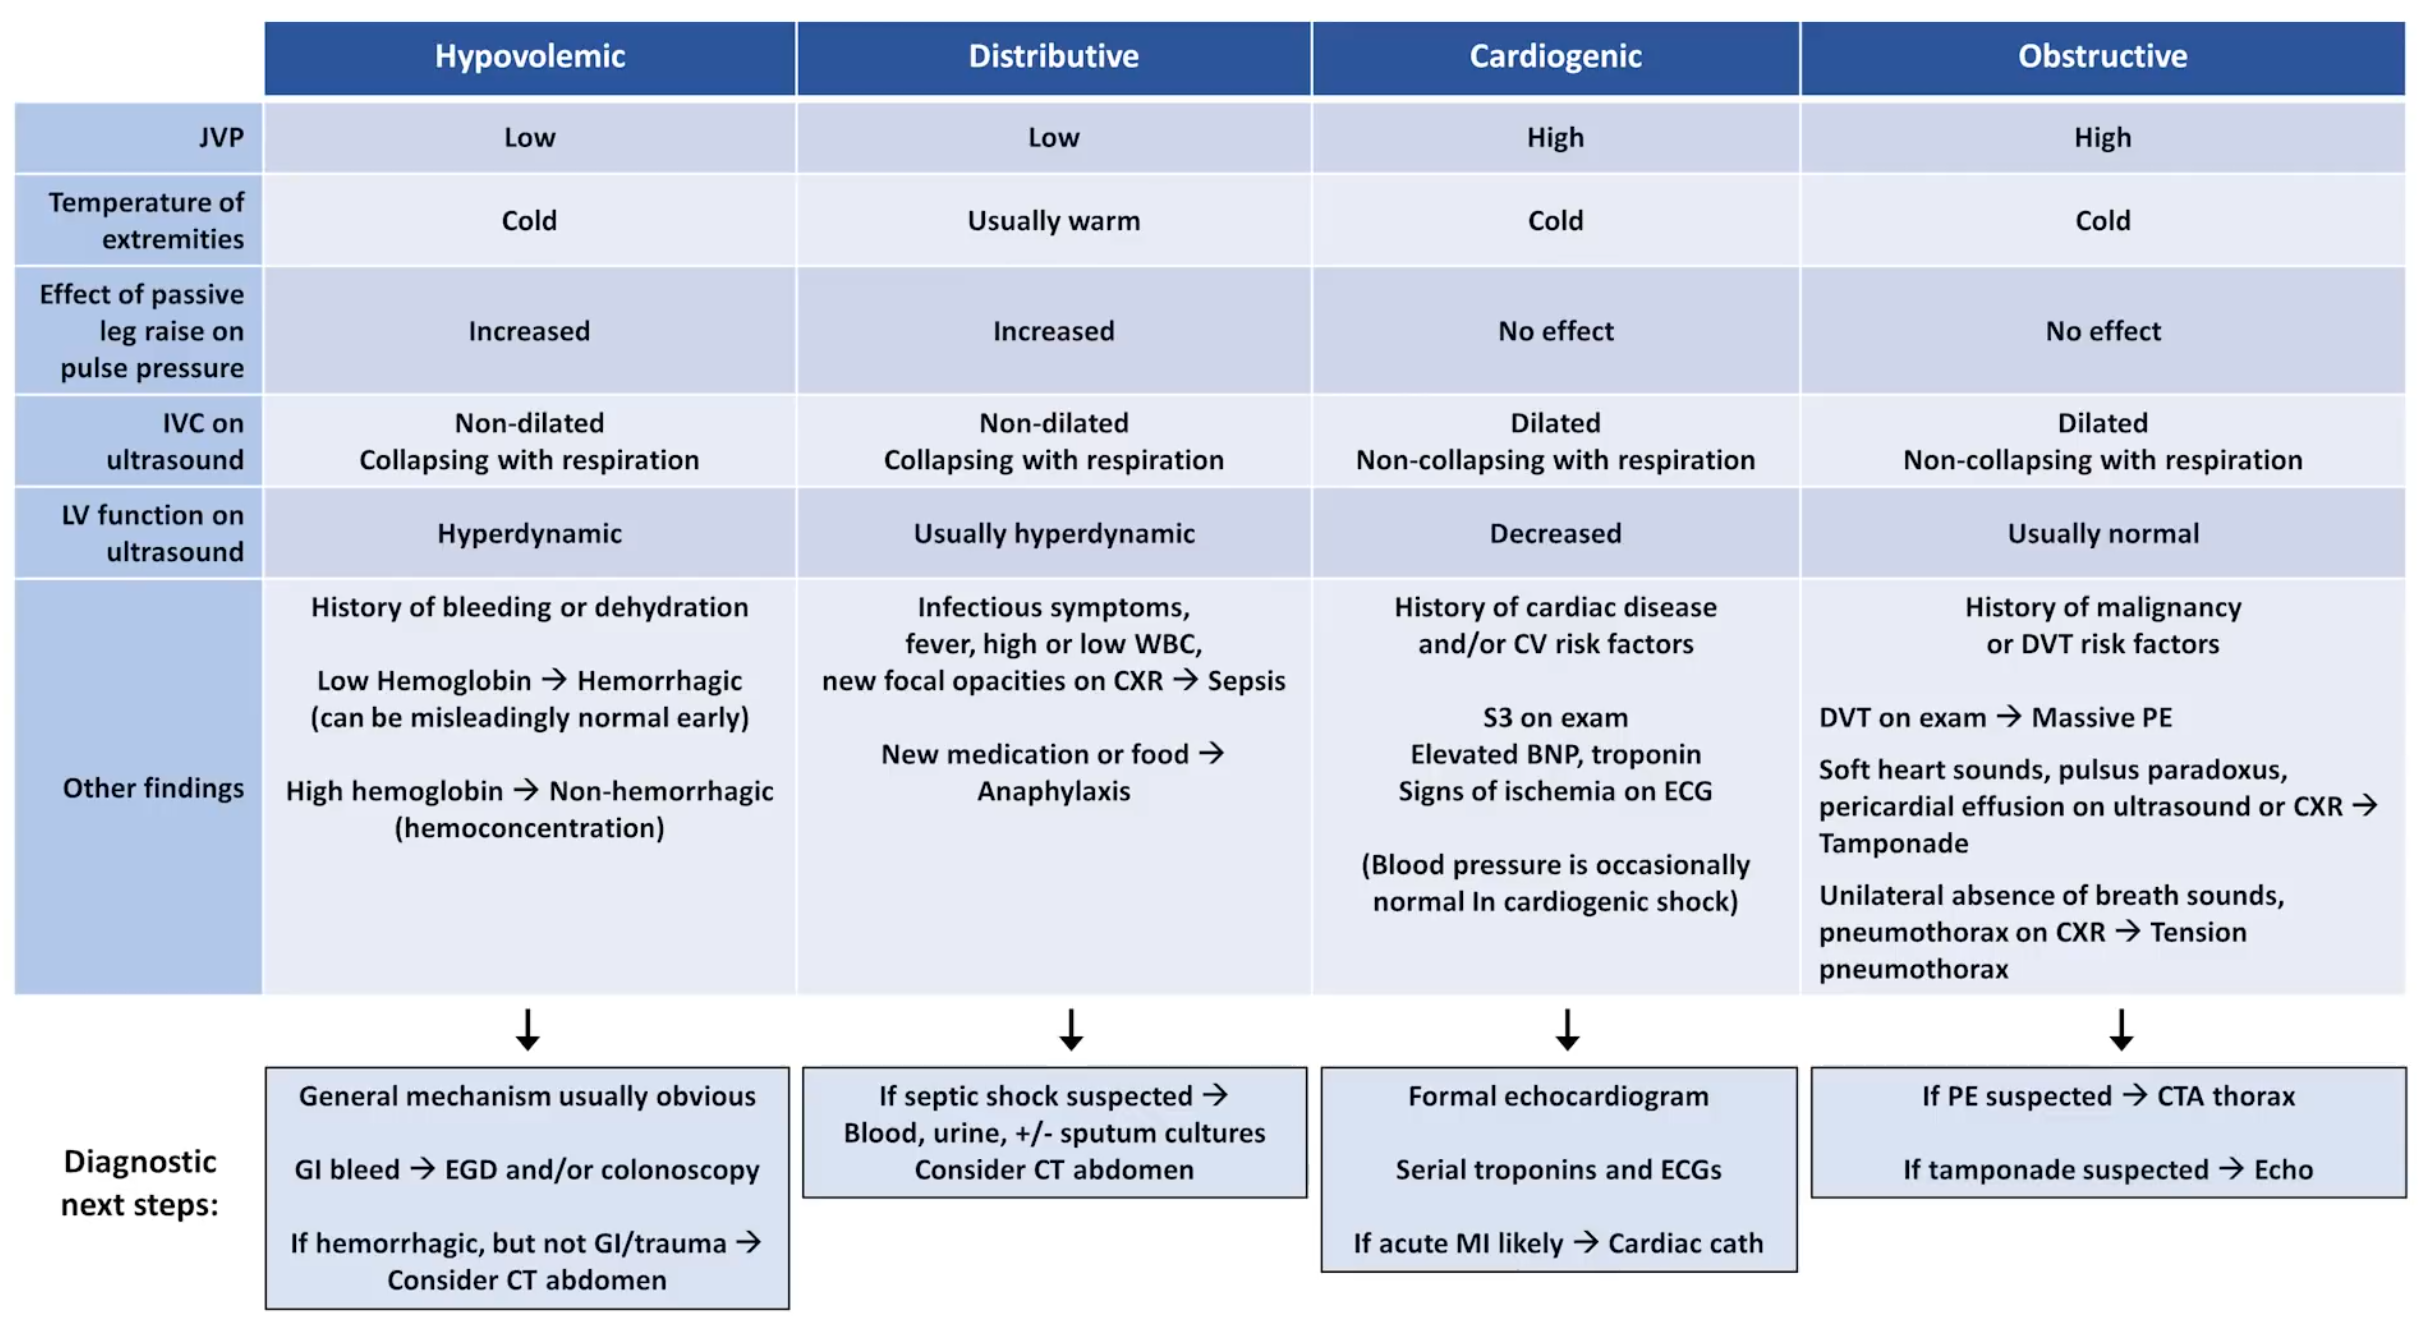
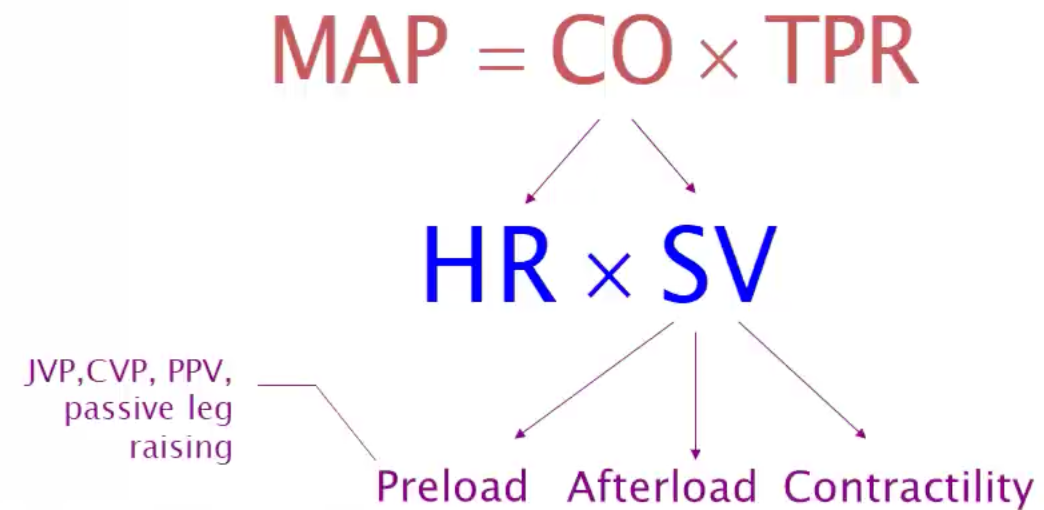
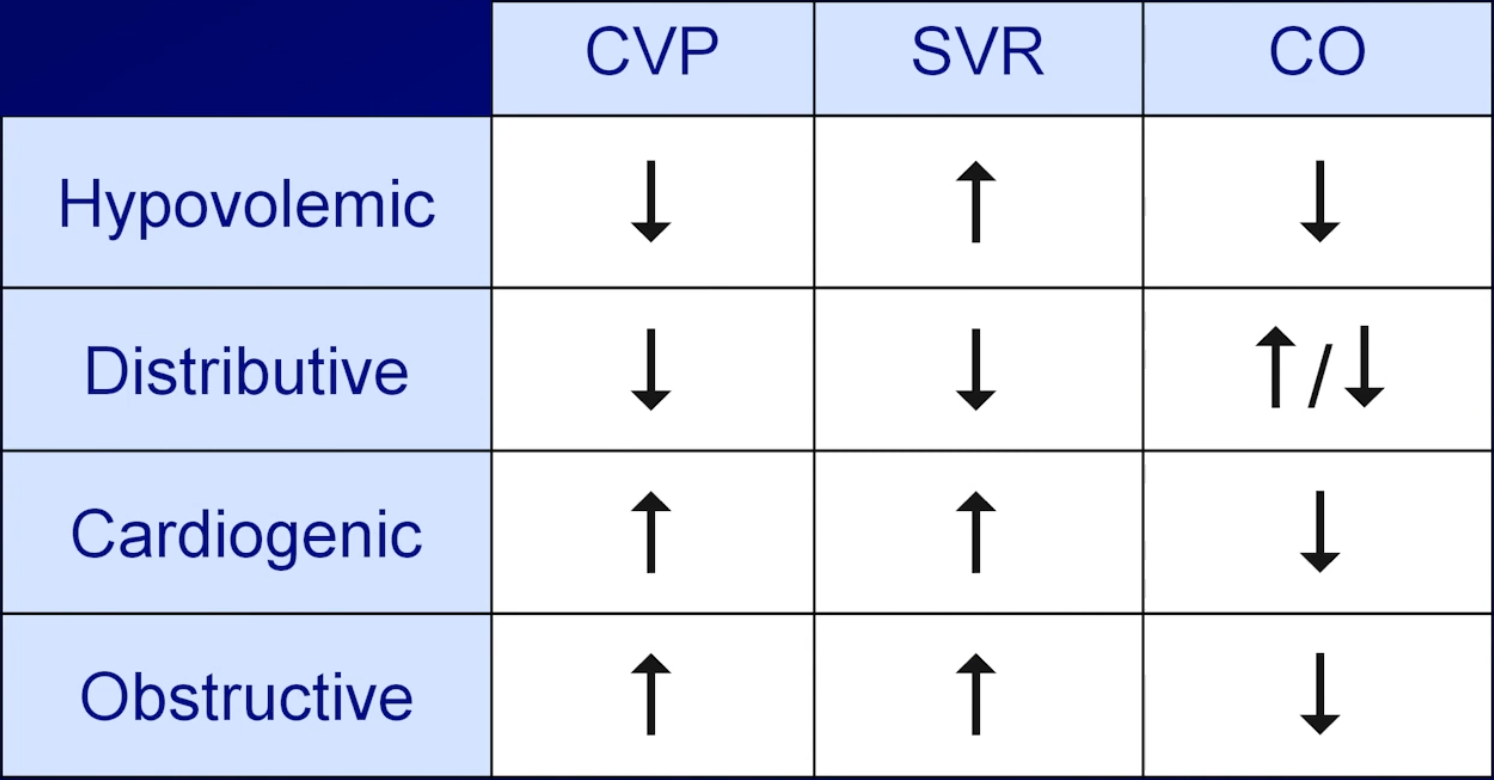
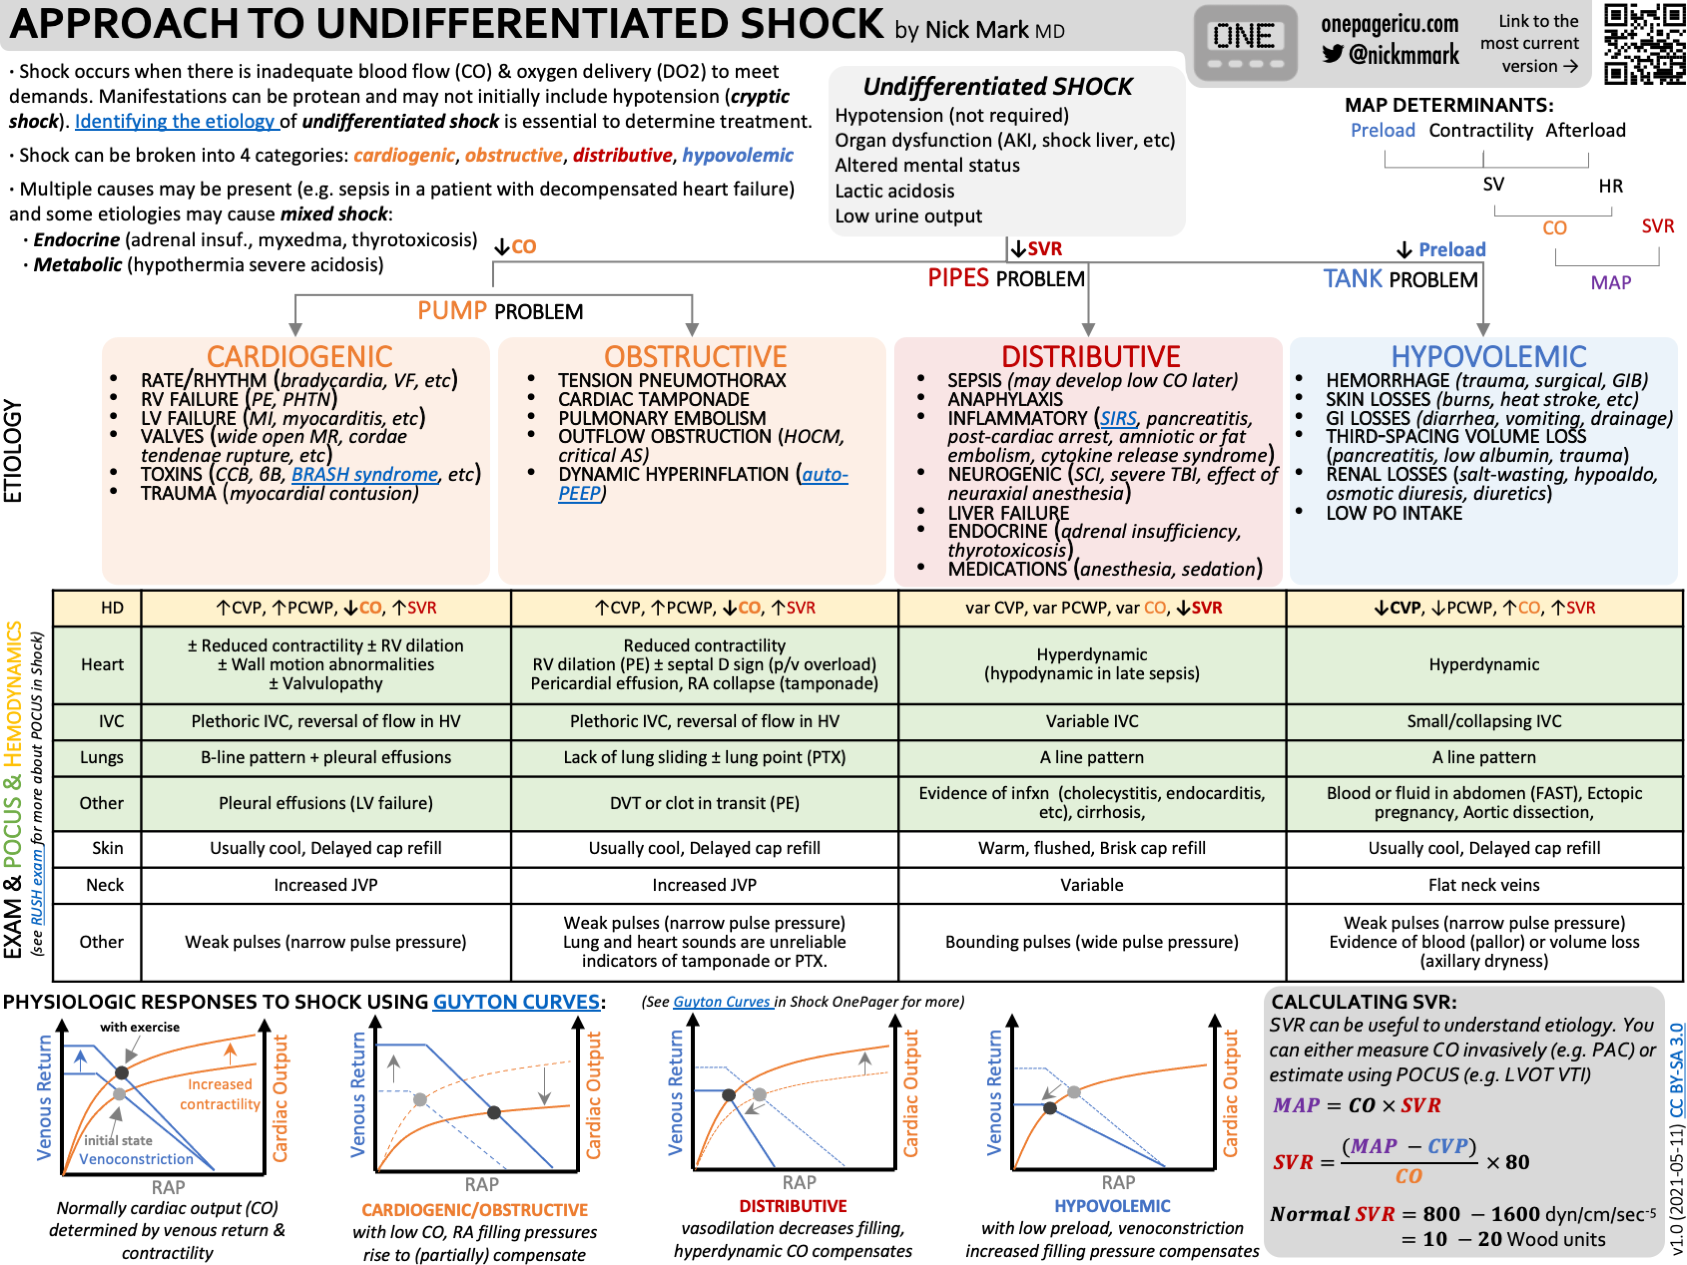
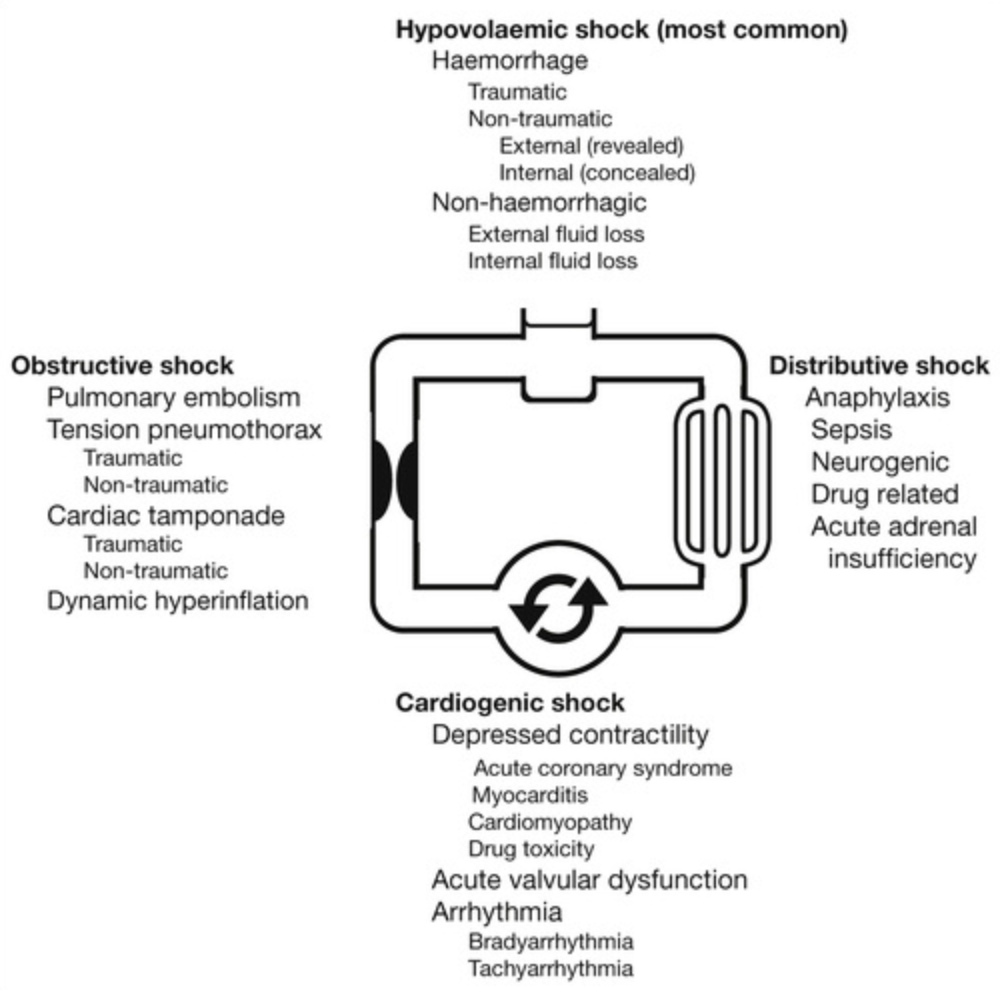
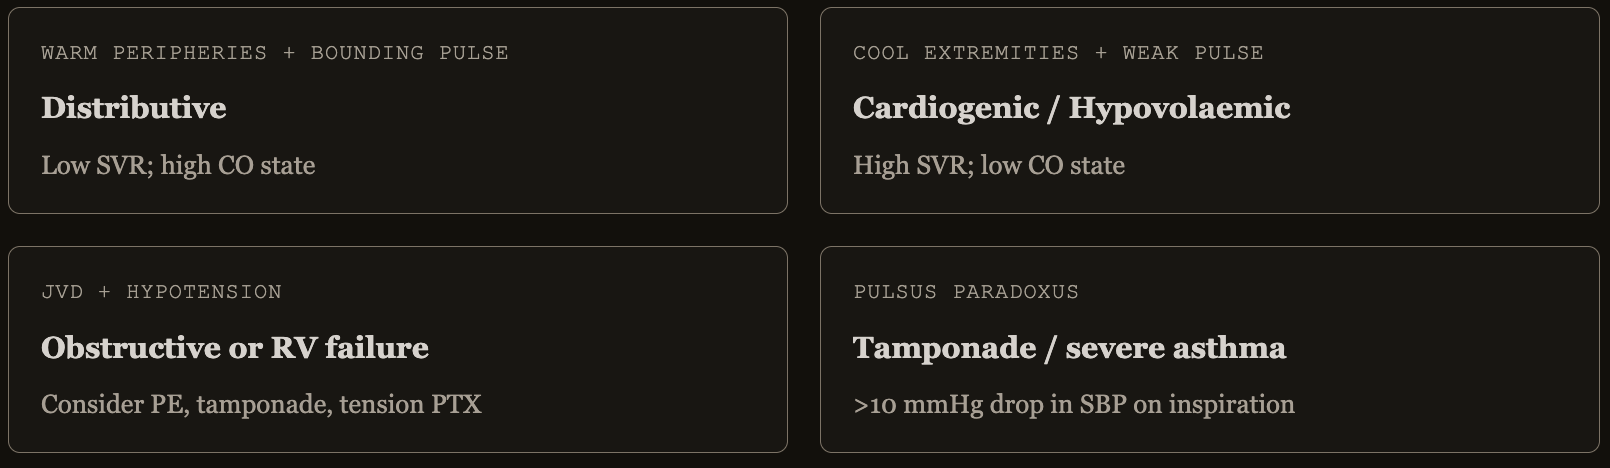
Main Assessment Factors to Differentiate Shock Types
- Peripheral perfusion (as a measure of TPR)
- Heart rate
- Preload status using JVP, CVP, PPV or response to passive leg raise
Overview of RUSH Exam
- Heart: LV function, RV dilation, pericardial effusion/tamponade
- IVC: size and collapsibility (volume responsiveness)
- Lungs: B-lines (pulmonary oedema), pneumothorax (absence of sliding)
- Abdomen: free fluid (haemoperitoneum, ruptured AAA)
- Aorta: AAA
- Lower limbs: DVT (if PE suspected)
Can use the mnemonic HI-MAP (Heart, IVC, Morrison’s pouch, Aorta, Pneumothorax) or alternatively go in the approach of pump (heart), tank (IVC, Morison’s pouch), and pipes (aorta, DVT)
- Establish venous access
- Collect a series of generic laboratory investigations, most importantly an ABG
- Mobile Chest X-ray
- Assess neurology (i.e. spinal injury)
- Exclude neurogenic (“spinal”) shock
- Exclude neurogenic (“spinal”) shock