Definition
- The purpose of an airway assessment is to predict and plan for a difficult airway
- The definition of a difficult airway1 is: “the clinical situation in which a conventionally trained Anaesthesiologist experiences difficulty with facemask ventilation, difficulty in supraglottic device ventilation, difficulty in tracheal intubation or all three” where:
- Difficulty with facemask ventilation is the inability of an unassisted anaesthesiologist:
- to maintain oxygen saturation, measured by pulse oximetry, 92%; or
- to prevent or reverse signs of inadequate ventilation during positive-pressure mask ventilation under general anaesthesia
- Difficult laryngoscopy occurs when “it’s not possible to visualise any portion of the vocal cords with conventional laryngoscopy”
- This typically corresponds to a Cormack and Lehane Grade IV laryngoscopy view
- Difficult endotracheal intubation occurs when “proper insertion of the tracheal tube with conventional laryngoscopy requires more than three attempts or more than 10 minutes”
- Difficulty with facemask ventilation is the inability of an unassisted anaesthesiologist:
Pre-Operative Airway Assessment
LEMON Screening Tool to Predict Difficult Laryngoscopy
- Look:
- Dose the patient look like the stereotypical difficult intubation
- Evaluate: 3:3:2 rule:
- 3 fingers width of mouth opening
- 3 fingers width of thyromental distance (from the thyroid cartilage to the mental process of the mandible)
- 2 fingers width of distance from the hyoid to the thyroid
- Mallampati score
- Obesity and obstruction
- Is the patient morbidly obese
- Is there some sort of obstruction (e.g. abscess)
- Neck mobility
BONES to Predict Difficult Bag Valve Mask Ventilation
- Beard
- Obesity
- No teeth
- Sleep apnoea or Snoring
Although the most valuable independent predictors of difficult mask ventilation as per RCoA analysis are: Age > 55 years, BMI > 26, lack of definition, facial hair, history of snoring. Alternatively MOANS can be used instead — mask seal features (e.g. beards, saliva or blood or anatomical features such as facial fractures or retrognathia), obesity, age > 55 years, no teeth, snoring or stiff
RODS to Predict Difficult Laryngeal Mask Airway Insertion
- Restricted mouth opening
- Obstruction; airway obstruction at or below the level of the glottis will not be relieved by the insertion of a supraglottic device
- Distorted airway: unusual airway anatomy may prevent the supraglottic device from seating properly
- Stiff lungs or c-spine/neck: decreased lung compliance (e.g. asthma) may make ventilation with a supraglottic device impossible and in patients with limited neck movement, the supraglottic device may form a poor seal
SHORT to Predict Difficult Surgical Airway
- Surgery of the neck
- Haematoma at the neck
- Obesity at the neck
- Radiation distortion or other deformity
- Tumour
The ANZCA document outlines the essential components of the routine airway assessment:
- Presence of any previous anaesthesia issues
- Presence of any gastric reflux
- Presence of any obstructive sleep apnoea
- Body mass index
- Mouth opening
- Modified Mallampati score
- Dental status
- Thyro-mental distance
- Jaw protrusion
- Cervical spine movemen
History
- General history elements:
- Reason for airway protection/management
- AMPLE history (allergies, medications, past medical history, last meal, events)
- Exercise capacity
- Smoker
- Symptoms or risk factors for airway compromise:
- Stridor, hoarse voice, orthopnoea, drooling, dysphagia
- Risk factors - suspecterd airway burn, neck trauma, goitre
- Risk factors for difficult airway management: infections of oropharynx and neck (e.g. Ludwig’s angina), problems with mouth opening (e.g. trauma, soft tissue disorders), problems with neck mobility (e.g. cervical spine disruption, rheumatoid arthritis, cervical fusion), , Obesity, OSA, oropharyngeal or neck masses, dentition, pregnancy, recent intubation, angioedema, burns
Chart Review
- Whenever possible identify:
- The patient’s previous intubation grade and previous difficulties with airway management
- Determine what techniques and manoeuvres were required to optimise airway management conditions
- History of airway-altering changes since the last anaesthetic (e.g. significant weight gain, C-spine surgery, head and neck radiotherapy etc.)
Examination
- General
- Level of consciousness and co-operation
- Level of comfort (i.e. can the patient be positioned properly, or are they too short of breath)
- BMI
- Pregnancy
- Face: facial hair, craniofacial deformities
- Mouth
- Mallampati grade (>2 predicts difficult airway)
- Mouth opening (inter incisor distance)
- Shape of palate (e.g. arched or narrow)
- Jaw protrusion and patient’s ability to prognath (voluntarily protrude the mandible)
- Teeth
- Teeth prominence
- Relaxation of maxillary to mandibular incisors during normal jaw closure
- Dentures/caps/grows/loose teeth
- Neck
- Range of motion of head and neck
- Thyro-mental distance <6cm
- Mandibulo-hyoid distance <4cm
- Sternomental distance <12cm
- Neck length and circumference/thickness
- Compliance of mandibular space
Investigations
- Investigations to consider:
- Neck ultrasound
- Nasal endoscopy
- Awake laryngoscopy
- Lateral neck x-ray
- Chest X-ray
- CT/MRI neck
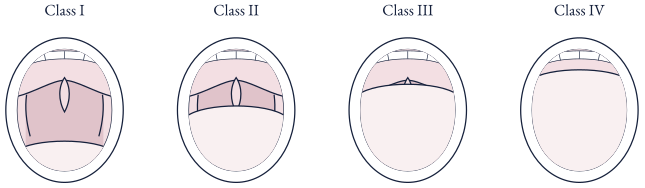
- Mallampati score
- Class I: Soft palate, uvula and faucial pillars visible
- Class II: Soft palate and faucial pillars visible with the uvula partially obscured by tongue
- Class III: Soft palate and base of uvula visible
- Class IV: Only hard palate visible
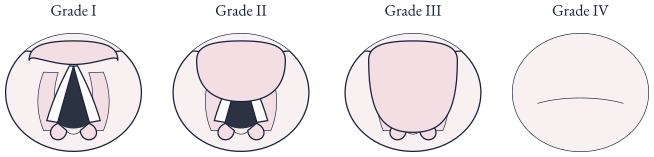
- Cormack-Lehane Classification
- Grade 1: Full view of glottis
- Grade 2a: Partial view of glottis
- Grade 2b: Only posterior extremity of glottis seen or only arytenoid cartilages
- Grade 3a: Epiglottis can be lifted from the posterior pharyngeal wall
- Grade 3b: Epiglottis cannot be lifted from the posterior pharyngeal wall
- Grade 4: Neither glottis nor epiglottis seen
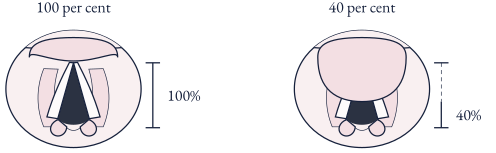
- Percentage of visible glottic opening (POGO)
- It requires the observer to estimate how much of the glottis is not visualised
Mnemonics
- Difficult intubation = LEMON
- Look externally
- Evaluate 3-3-2 rule
- Mallampati score
- Obstruction
- Neck Mobility
- Difficult BVM = BONES
- Beard
- Obese
- No teeth
- Elderly
- Sleep Apnea / Snoring
- Difficult surgical airway = SHORT
- Surgery
- Hematoma
- Obesity
- Radiation distortion or other deformity
- Tumor
Other Notes
The ANZCA document outlining airway assessment describes it being mandatory to provide written information to the patient and their medical practitioner when a difficult airway is encountered as well as advice for them to get a medical alert bracelet.
Determining an Airway Management Plan
There are nine core airway management considerations:
- Is there information about any previous airway difficulties?
- Is there any altered cardiorespiratory physiology?
- What is the impact of the surgery on the airway?
- How difficult will it be to bag-and mask ventilate?
- How difficult is it to place a supraglottic airway?
- How difficult will it be to intubate the patient?
- How difficult will it be to perform an infraglottic airway?
- What is the risk of aspiration?
- How easy will they be to extubate safely?
Sources
- Airway Assessment • LITFL Medical Blog • CCC Airway - Chris Nickson - Updated July 1 2024 - Accessed 28 August 2026
- Airway Assessment - ANZCA - Bradley, P., Chapman, G., Crooke, B., Greenland, K August 2016 - Accessed 28 August 2026
- Recognition of the anatomically difficult airway - Deranged Physiology - Alex Yartsev - Last Updated 17/07/2026 - Accessed 24 September 2026
Footnotes
-
More on the definition of the anatomically difficult airway can be read at Recognition of the anatomically difficult airway ↩